Sunday, January 28, 2007
daphne 2nd posting for dPBL- ATHLETE'S FOOT

Athlete foot is caused by the ringworm fungus ("tinea" in medical jargon). Athlete foot is also called tinea pedis. The fungus that causes Athlete foot can be found on floors and in socks and clothing. The fungus can be spread from person to person by contact with these objects. However, without proper growing conditions (a warm, moist environment), the fungus will not infect the skin. Up to 70% of the population will have athletes foot at some time during their lives.
When the skin is injured by the fungus, bacteria can also invade the skin. These bacteria can cause a bad smell. Bacterial infection of the skin and resulting inflammation is known as cellulitis. This is especially likely to occur in the elderly, individuals with diabetes, chronic leg swelling, or who have had veins removed (such as for heart bypass surgery), and patients with impaired immune systems.
The second part of treatment is the use of antifungal creams. Many medications are available including miconazole, clotrimazole, etc.
Friday, January 19, 2007
Parasites
In the jungle, soldiers are very prone to diseases. These diseases can be contagious and can spread within a platoon. Below are the some of the most common parasites that cause diseases.
Sporozoa
1.Plasmodium
Plasmodium is a genus of parasitic protozoa. Infection with this genus is known as malaria. The parasite always has two hosts in its life cycle: a mosquito vector and a vertebrate host.
There are 4 different Plasmodium species known at the moment ;
P.Falciparum
P.Vivax
P.Malariae
P.Ovale
The life cycle of Plasmodium is very complex. Sporozoites from the saliva of a biting female mosquito are transmitted to either the blood or the lymphatic system of the recipient. Mosquitoes of the genera Culex, Anopheles, Culiceta, Mansonia and Aedes may act as vectors. The currently known vectors for human malaria (> 100 species) all belong to the genus Anopheles.
Mode of transmission
Transmission is by the female Anopheles mosquito whereby the sporozoites in the saliva of the mosquito are injected into humans and attacks the hepatocytes. Since these mosquitoes can be found in tropics and sub tropics, Brunei is one country this parasite can be found. It provides the suitable climate for mosquitoes.
Symptoms
Fever
Anaemia
Largescale intravascular hemolysis
Could even lead to cerebral malaria
Diagnosis
Thick smear is done for screening
THick smear helps to consolidate large amount of red blood cells in a small area
thus making the detection much simpler.
Thin smear is done for confirmatory of species
After a positive thick smear, a thin smear is done and the Plasmodium species are identified.
Interpretations of the results
P.falciparum
Usually has more than 1 ring in the red cell. The rings are usually 1/5 the size of the red cell.
It has 2 chromatin granules and its gametocytes are shoe-shaped. It does not cause the red cell to enlarge.
P.vivax
The rings are usually 1/3 or 1/2 the size of the red cell. It causes the red cell to enlarge. It only has 1 chromatin granule. Its gametocytes are usually round.
Serology
Confirmation of detection can be done serologically. Dipsticks containing the monoclonal antibodies to the parasites seek out the antigens of the parasite.
Prevention
Chemoprophylaxis to travellers
Mosquito net, window screens, protective clothing & insect repellents
Drainage of stagnant water reduces the breeding areas
Treatment
Chloroquine kills sensitive strains
Primaquine prevent relapses (eg. P vivax)
Mefloquine or quinine & doxycline kill chloroquine resistant P. falciparum
2. Toxoplasma gondii
Toxoplasma is a genus of parasitic protozoa whose definitive host is cats but which can be carried by the vast majority of warm-blooded animals, including humans. Toxoplasmosis, the disease it causes, is usually minor and self-limiting but can have serious or even fatal effects on a fetus whose mother first contracts the disease during pregnancy or on an immunocompromised human or cat. (http://en.wikipedia.org/wiki/Toxoplasma_gondii)
Mode of transmission
Animals and humans that ingest oocysts (e.g., by eating unwashed vegetables etc.) or tissue cysts in improperly cooked meat become infected. The parasite enters macrophages in the intestinal lining and is distributed via the blood stream throughout the body.
Diagnosis
Immunofluorescent to detect presence of IgM, IgG
Microscopic examination of Giemsa stained smears of tissues. Crescent-shaped trophozoites are observed.
Treatment
Sulfaziadine
pyrimethamine
Prevention
Cook meat thoroughly
wash vegetables thorougly
3. Entamoeba histolytica
Entamoeba histolytica is an anaerobic parasitic eukaryotic protozoa, part of the genus Entamoeba. It infects predominantly humans and other primates. Diverse mammals such as dogs and cats can become infected but usually do not shed cysts (the environmental survival form of the organism) with their feces, thus do not contribute significantly to transmission. The active ring stage exists only in the host and in fresh feces; cysts survive outside the host in water and soils and on foods, especially under moist conditions on the latter. When swallowed they cause infections by excysting (to the trophozoite stage) in the digestive tract.
(http://en.wikipedia.org/wiki/Entamoeba_histolytica)
Mode of transmission
Ingestion of cysts transmitted by the fecal oral route in contaminated food and water. It works by boring through the enteric walls and can reach the blood stream. From there, it can reach different vital organs of the human body, like the liver, lungs, brain, eyes etc.
Symptoms include
fulminating dysentary,
diarrhea,
weight loss,
fatigue,
abdominal pain,
amebomas
Diagnosis
Observing stool samples under the microscope shall show trophoziotes of cysts presence.
Prevention
Avoid fecal contamination of food & water
Good personal hygiene such as hand washing
Purification of water supply
Cooking of vegetables
Treatment
Metronidazole
3. Giardia lamblia
Giardia lamblia (formerly also Lamblia intestinalis and also known as Giardia duodenalis and Giardia intestinalis) is a flagellated protozoan parasite that infects the gastrointestinal tract and causes giardiasis.
(http://en.wikipedia.org/wiki/Giardia_lamblia)
Mode of transmission
Infection from giardia can occur from consuming contaminated food or water; this includes clean-looking mountain streams. It can also be transferred from animal or human feces.Giardia infection is a concern for people camping in the wilderness or swimming in contaminated streams or lakes. Giardia may be ingested at camping areas, day care centers, waterborne outbreaks, and is also highly infectious to other family members once one individual is infected. Other causes can be uncooked food, contaminated wells and failed municipal water sytems.
Ingestion of cysts transmitted by the fecal oral route in contaminated food and water
Pathogenesis
The life cycle consists of a noninfected cyst being excreted out through feces of an infected individual. Once out in the environment, the cyst becomes infected. A distinguishing characteristic of the cyst is 4 nuclei and a retracted cytoplasm. Once ingested by a host, the trophozoite emerges to an active state of feeding and motility. It feeds on mucous inside the digestive tract and causes the host to have epigastric pain, excessive gas, and diarrhea with fat and mucous but no blood. This can last from 2 - 4 weeks but for a lactose intolerant individual, it can last up to six months.
After the feeding stage, the trophozoite undergoes asexual replication through longitudinal binary fission. The resulting trophoziotes and cysts then pass through the digestive system in the feces
Symptoms
nonbloody,
foul-smelling diarrhea,
nausea, anorexia,
flatulence,
abdominal cramps
Diagnosis
Stool samples will show giardia cysts which often looks like 'clown face'.
Treatment
Metronidazole or quinacrine hydrochloride
Prevention
Drinking boiled, filtered, iodine treated water in endemic areas
Cryptosporidium
Cryptosporidium is a protozoan pathogen of the Phylum Apicomplexa and causes a diarrheal illness called cryptosporidiosis. Cryptosporidium is capable of completing its life cycle within a single host, resulting in cyst stages which are excreted in feces and are capable of transmission to a new host. Cryptosporidium has a spore phase (oocyst) and in this state can survive for lengthy periods outside a host and also can resist many common disinfectants, notably chlorine based disinfectants. Because of this resistance, water purification to eliminate Cryptosporidium generally relies upon coagulation followed by filtration or boiling.
(http://en.wikipedia.org/wiki/Cryptosporidium)
Mode of transmission
Transmission can be due to drinking contaminated water or dealing with infected fecal material.
Diagnosis
Stool samples will show Cryptosporidium cysts under the microscope.
Prevention
Treat water with UV light or boil it before consumption.
Helminths
Taenia solium, also called the pork tapeworm. It is a cyclophyllid cestode in the family Taeniidae. It infects pigs and humans in Asia.
(http://en.wikipedia.org/wiki/Taenia_solium)
Taenia saginata, also known as Taeniarhynchus saginata or the Beef tapeworm, is a parasite of both cattle and humans, but which can only reproduce in humans. (http://en.wikipedia.org/wiki/Taenia_saginata)
Mode of transmission
infection is caused by ingestion of eggs
ingestion of uncooked meat
introduction to fungal infections- daphne
Introduction: Fungal Infections
Fungi and yeasts are multi-celled plants that are parasites. An everyday example of a fungus is mushrooms. However, the fungi that cause human disease are usually very small fungi. There are a few common human fungal conditions that are rarely harmful except for those with severely weakened immune systems. (Source: WD Writers)
A fungus is actually a primitive vegetable. Fungi can be found in air, in soil, on plants, and in water. Thousands, perhaps millions, of different types of fungi exist on Earth. The most familiar ones to us are mushrooms, yeast, mold, and mildew. Some live in the human body, usually without causing illness. In fact, only about half of all types of fungi cause disease in humans. Those conditions are called mycoses. (Source: excerpt from Microbes in Sickness and in Health - Publications, National Institute of Allergy and Infectious Diseases: NIAID)
Definitions of Fungal Infections:
A kingdom of eukaryotic, heterotrophic organisms that live as saprobes or parasites, including mushrooms, yeasts, smuts, molds, etc. They reproduce either sexually or asexually, and have life cycles that range from simple to complex. Filamentous fungi refer to those that grow as multicellular colonies (mushrooms and molds).
Symptoms of fungal infections
Some of the symptoms of Fungal infections incude:
-Alopecia : various types of hair loss or balding
-Annular lesions
-Pustules : Small elevated pus containing lesion of the skin.
-Rash
-Onycholysis : Loosening or loss of part or all of nail.
Name and Aliases of Fungal Infections:
Main name of condition: Fungal infections
Other names or spellings for Fungal infections:
Fungi, Fungus, Fungal disease, Fungal diseases, Fungal condition, Fungal conditions, Mycoses, Mycosis, fungi, fungus Source - WD Writers
Types of Fungal Infections:
Subtypes of Fungal infections: Candida, Vaginal Candidiasis, Oral thrush, Athlete's foot, Tinea, Yeast infections, Ringworm, Allergic bronchopulmonary aspergillosis, Aspergillosis, Cryptococcal, Meningitis, Fungal nail infections, Histoplasmosis, invasive candidiasis, Mycetoma, Cryptococcosis, Sporotrichosis, Pityriasis Versicolor, Zygomycosis
Disease Category: Parasite.fungal
Parasite.fungal: Diseases caused by fungi Introduction: Fungi and yeasts are multi-celled plants that are parasites. An everyday example of a fungus is mushrooms. However, the fungi that cause human disease are usually very small fungi. There are a few common human fungal conditions that are rarely harmful except for those with severely weakened immune systems. Some examples are Candida (thrush), Yeast infections, Tinea (Athlete's foot), and Ringworm.
Risk Factors for Fungal infections
Risk factors for Fungal infections are factors that do not seem to be a direct cause of the disease, but seem to be associated in some way. Having a risk factor for Fungal infections makes the chances of getting a condition higher but does not always lead to Fungal infections. The list of risk factors mentioned for Fungal infections in various sources includes: Damaged skin, Moist skin, Broad-spectrum antibiotics, Immunocompromise, AIDS and Chronic disease.
Thursday, January 18, 2007
PBL Package 2
Introduction to Fungi
Fungi are plant-like organisms that lack chlorophyll. Fungi are one of the 5 kingdoms of life. Many fungi are good and useful (edible mushrooms would be an example of these) while some cause problems (some fungi can injure plants and people). Since they do not have chlorophyll, fungi must absorb food from others. Since they don't use light to make food, fungi can live in damp and dark places. Fungi are supposed to "eat" things when they are dead but sometimes they start eating when the organism is still alive.
To cure fungal infections, mycologists use a drug from one of these families of drugs: Allylamines, antimetabolites, azoles, glucan synthesis inhibitors, polyenes, and others. Finally, fungi can be helpful and not helpful, but they all are important and required in life. Fungi are one of the earth's big recyclers. Without them we could not live, and sometimes humans die because of them, but they are very important and required in life.
www.doctorfungus.org/index.htm> General Discussion> Introduction to Fungi
Classification of medically important fungi is based on morphology, namely filamentous fungi, yeast and dimorphic fungi.
- Filamentous Fungi (Moulds)
Examples of medically important filamentous fungi associated in this case are:
1) Dermatophytes
A dermatophyte is a parasitic fungus upon the skin. The term embraces the imperfect fungi of the genera Epidermophyton, Microsporum and Trichophyton.
Epidermophyton - produces only macroconidia, no microconidia and consists of 2 species, one of which is a pathogen.
Microsporum - Both microconidia and rough-walled macroconidia characterize Microsporum species. There are 19 described species but only 9 are involved in human or animal infections.
Trichophyton - When produced the macroconidia of Trichophyton species are smooth-walled. There are 22 species, most causing infections in humans or animals.
http://www2.provlab.ab.ca/bugs/webbug/mycology/dermhome.htm> What are dermatophytes?
Dermatophytes cause infections of the skin, hair and nails due to their ability to obtain nutrients from keratinized material. The organisms colonize the keratin tissues and inflammation is caused by host response to metabolic by-products. They are usually restricted to the nonliving cornified layer of the epidermis because of their inability to penetrate viable tissue of an immunocompetent host. Invasion does elicit a host response ranging from mild to severe. Acid proteinases, elastase, keratinases, and other proteinases reportedly act as virulence factors. The development of cell-mediated immunity correlated with delayed hypersensitivity and an inflammatory response is associated with clinical cure, whereas the lack of or a defective cell-mediated immunity predisposes the host to chronic or recurrent dermatophyte infection.
Some of these infections are known as ringworm or tinea. Toe- and fingernail infection are referred to as onychomycosis. Dermatophytes usually do not invade living tissues, but colonize the outer layer of the skin. Occasionally the organisms do invade subcutaneous tissues, resulting in kerion development.
Identification
Microscopic morphology of the micro and macroconidia is the most reliable identification character, but a good slide preparation is needed, and also needed is the stimulation of sporulation in some strains. Culture characteristics such as surface texture, topography and pigmentation are variable so they are the least reliable criteria for identification. Clinical information such as the appearance of the lesion, site, geographic location, travel history, animal contacts and race is also important, especially in identifying rare non-sporulating species like Trichophyton concentricum, Microsporum audouinii and Trichophyton schoenleinii.
Transmission
Dermatophytes are transmitted by direct contact with infected host (human or animal) or by direct or indirect contact with infected exfoliated skin or hair in clothing, combs, hair brushes, theatre seats, caps, furniture, bed linens, towels, hotel rugs, and locker room floors. Depending on the species the organism may be viable in the environment for up to 15 months. There is an increased susceptibility to infection when there is a preexisting injury to the skin such as scars, burns, excessive temperature and humidity. Adaptation to growth on humans by most geophilic species resulted in diminished loss of sporulation, sexuality, and other soil-associated characteristics.
http://en.wikipedia.org/wiki/Main_Page> Search> Dermatophytes
Lab Diagnosis
a) Specimens are obtained from skin scales, nail scraping and hair
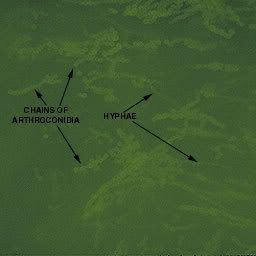
b) Mircoscopy is carries out using KOH preparation of Hypae
- A small sample of the specimen is selected for direct microscopic examination and investigated for the presence of fungal elements.
- The specimen is mounted in a small amount of potassium hydroxide or calcofluor white.
- The KOH slides are gently heated and allowed to clear for 30 to 60 minutes before examining on a light or phase contrast microscope.
- Calcofluor white slides are examined on a fluorescent microscope.
c) When cultured on fungal media, Myeceliuma and asexual spores are observed
- Nails are scraped or minced into small pieces
- Hair is cut into short segments
- specimen is divided between at least two types of culture media
- The use of antibiotics will inhibit the overgrowth of bacteria and incorporation of cycloheximide will prevent the overgrowth of the rapidly growing saprophytic fungi
- The cultures are incubated at 30°C and examined frequently for 4 weeks
http://www2.provlab.ab.ca/bugs/webbug/mycology/dermhome.htm> Specimen Collection & Microscopic Method
Treatment Against Dermatophytes can be carried out using:
- Topical azoles (eg. Miconozole, clotrimazole
- Griseofulvin for tinea capitis
Keeping the skin dry and cool aids in the prevention of dermatophytes.
2) Zygomycetes
Zygomycetes are usually fast growing fungi characterized by primitive coenocytic (mostly aseptate) hyphae. Asexual spores include chlamydoconidia, conidia and sporangiospores contained in sporangia borne on simple or branched sporangiophores. Sexual reproduction is isogamous producing a thick-walled sexual resting spore called a zygospore.
Identification
Most isolates are heterothallic i.e. zygospores are absent, therefore identification is based primarily on sporangial morphology. This includes the arrangement and number of sporangiospores, shape, color, presence or absence of columellae and apophyses, as well as the arrangement of the sporangiophores and the presence or absence of rhizoids. Growth temperature studies (25,37,45oC) can also be helpful. Tease mounts are best, use a drop of 95% alcohol as a wetting agent to reduce air bubbles.
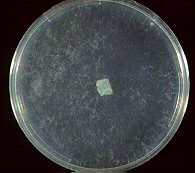
Agar block method to induce sporulationof Apophysomyces elegans
Taken from : http://www.mycology.adelaide.edu.au/Fungal_Descriptions/Zygomycetes/Apophysomyces/index.html
Laboratory identification of some zygomycetous fungi, especially Apophysomyces elegans and Saksenaea vasiformis may be difficult or delayed because of the mould's failure to sporulate on the primary isolation media or on subsequent subculture onto potato dextrose agar. Sporulation may be stimulated by the use of nutrient deficient media, like cornmeal-glucose-sucrose-yeast extract agar, Czapek Dox agar.
Examples of Zygomycetes
a) Apophysomyces elegans
- Colonies are fast growing, white becoming creamy white to buff with age, downy with no reverse pigment, and are composed of broad, sparsely septate (coenocytic) hyphae typical of a zygomycetous fungus.
- Sporangiophores are unbranched, straight or curved, slightly tapering towards the apex, up to 200 um long, 3-5 um in width near the apophysis, and hyaline when young but developing as the culture ages, a sepia to brown pigmentation and a conspicuous sub-apical thickening 10-16 um below the apophysis with age.
- Sporangiophores arise at right angles from the aerial hyphae and often have a septate basal segment resembling the "foot cell" commonly seen in Aspergillus.
- Rhizoids are thin-walled, sub-hyaline and predominantly unbranched.
- Sporangia are multispored, small (20-50 in diameter), typically pyriform in shape, hyaline at first, sepia colored when mature, columellate and strongly apophysate. Columellae are hemispherical in shape and the apophyses are distinctively funnel- or bell-shaped.
- Sporangiospores are smooth-walled, mostly oblong, occasionally subglobose, (3-4 x 5-6 um) and sub-hyaline to sepia in mass.
- Good growth at 26, 37 and 42C.
Clinical Significance
Culture of Saksenaea vasiformis.
Laboratory identification of some zygomycetous fungi, especially Apophysomyces elegans and Saksenaea vasiformis may be difficult or delayed because of the mould's failure to sporulate on the primary isolation media or on subsequent subculture onto potato dextrose agar. Sporulation may be stimulated by the use of nutrient deficient media, like Czapek Dox agar, cornmeal-glucose-sucrose-yeast extract agar, or by using the agar block method described by Ellis and Ajello (1982) and Ellis and Kaminski (1985).
Briefly, a small block of agar is cut from a well established culture grown on PDA and is placed in the centre of petri dish containing 1% agar in distilled water. After 21 days at 26C look for sporangium formation at the periphery of the petri dish.
Saksenaea vasiformis is a rare human pathogen that has also been associated with invasive lesions following traumatic implantation of the fungus and rhinocerebral, cutaneous and disseminated types of infection have also been reported. S. vasiformis appears to have a world-wide distribution in association with soil.
http://www.mycology.adelaide.edu.au/> Fungal Descriptions> Zygomycetes
-nora-
1. Aspergillus
Description and Natural Habitats
Aspergillus is a filamentous, cosmopolitan and ubiquitous fungus found in nature. It is commonly isolated from soil, plant debris, and indoor air environment. While a teleomorphic state has been described only for some of the Aspergillus spp., others are accepted to be mitosporic, without any known sexual spore production.
Species
The genus Aspergillus includes over 185 species. Around 20 species have so far been reported as causative agents of opportunistic infections in man. Among these, Aspergillus fumigatus is the most commonly isolated species, followed by Aspergillus flavus and Aspergillus niger. Aspergillus clavatus, Aspergillus glaucus group, Aspergillus nidulans, Aspergillus oryzae, Aspergillus terreus, Aspergillus ustus, and Aspergillus versicolor are among the other species less commonly isolated as opportunistic pathogens. See the list of obsolete names and synonyms for older names of these species.
The color of the colony in various Aspergillus species

2. Malassezia furfur
Description and Natural Habitats
Malassezia is a lipophilic yeast found on skin and body surfaces of humans and animals. It has been shown that colonization with Malassezia may occur as early as neonatal period [794]. It is a member of the normal skin flora in as much as 90% of adults and may occasionally cause superficial and deep mycoses. Malassezia has no known teleomorphic phase.
Species
There are seven proposed species in the genus Malassezia based on molecular, morphological, and biochemical profiles [277, 929, 953, 1369, 2087, 2407]. The most common and well-known species are Malassezia furfur and Malassezia pachydermatis [1223]. See the complete list of active species and summary of synonyms for the Malassezia spp.
In humans, the species causing skin disease, including the most common cause of dandruff and tinea versicolor is Malassezia furfur. The skin rash of tinea versicolor (pityriasis versicolor) is due to infection by this fungi, and is also thought to be involved in the skin condition of seborrhoeic dermatitis.
As the fungus requires fat to grow, it is most common in areas with many sebaceous glands: on the scalp, face, and upper part of the body. When the fungus grows too rapidly, the natural renewal of cells is disturbed and dandruff appears with itching (a similar process may also occur with other fungi or bacteria).
Feferences
1. Doctor Fungus. Retrieved on-line: http://www.doctorfungus.org/thefungi/malassezia_furfur.htm
2. Wikipedia. Retrieved on-line: http://en.wikipedia.org/wiki/Malassezia_furfur
Tuesday, January 9, 2007
Alvin
Pseudomonas aeruginosa
Pseudomonas aeruginosa is a Gram-negative rod measuring 0.5 to 0.8 µm by 1.5 to 3.0 µm. Almost all strains are motile by means of a single polar flagellum.
The bacterium is ubiquitous in soil and water, and on surfaces in contact with soil or water. Its metabolism is respiratory and never fermentative, but it will grow in the absence of O2 if NO3 is available as a respiratory electron acceptor.
The typical Pseudomonas bacterium in nature might be found in a biofilm, attached to some surface or substrate, or in a planktonic form, as a unicellular organism, actively swimming by means of its flagellum. Pseudomonas is one of the most vigorous, fast-swimming bacteria seen in hay infusions and pond water samples.
In its natural habitat Pseudomonas aeruginosa is not particularly distinctive as a pseudomonad, but it does have a combination of physiological traits that are noteworthy and may relate to its pathogenesis.
· Pseudomonas aeruginosa has very simple nutritional requirements. It is often observed "growing in distilled water" which is evidence of its minimal nutritional needs. In the laboratory, the simplest medium for growth of Pseudomonas aeruginosa consists of acetate for carbon and ammonium sulfate for nitrogen.
· P. aeruginosa possesses the metabolic versatility for which pseudomonads are so renowned. Organic growth factors are not required, and it can use more than seventy-five organic compounds for growth.
· Its optimum temperature for growth is 37 degrees, and it is able to grow at temperatures as high as 42 degrees.
· It is tolerant to a wide variety of physical conditions, including temperature. It is resistant to high concentrations of salts and dyes, weak antiseptics, and many commonly used antibiotics.
· Pseudomonas aeruginosa has a predilection for growth in moist environments, which is probably a reflection of its natural existence in soil and water.
These natural properties of the bacterium undoubtedly contribute to its ecological success as an opportunistic pathogen. They also help explain the ubiquitous nature of the organism and its prominance as a nosocomial pathogen.
P. aeruginosa isolates may produce three colony types. Natural isolates from soil or water typically produce a small, rough colony. Clinical samples, in general, yield one or another of two smooth colony types. One type has a fried-egg appearance, which is large, smooth, with flat edges and has an elevated appearance. Another type, frequently obtained from respiratory and urinary tract secretions, has a mucoid appearance, which is attributed to the production of alginate slime. The smooth and mucoid colonies are presumed to play a role in colonization and virulence.
Pseudomonas aeruginosa on MacConkey agar
E.coli
E. coli is the head of the large bacterial family, Enterobacteriaceae, the enteric bacteria, which are faculatively anaerobic Gram-negative rods that live in the intestinal tracts of animals in health and disease. The Enterobacteriaceae are among the most important bacteria medically. A number of genera within the family are human intestinal pathogens (e.g. Salmonella, Shigella, Yersinia). Several others are normal colonists of the human gastrointestinal tract (e.g. Escherichia, Enterobacter, Klebsiella), but these bacteria, as well, may occasionally be associated with diseases of humans.
The Enterobacteriaceae are distinguished from the Pseudomonadaceae in a number of ways known reflexively to competent microbiologists. The pseudomonads are respiratory, never fermentative, oxidase-positive, and motile by means of polar flagella. The enterics ferment glucose producing acid and gas, are typically oxidase-negative, and when motile, produce peritrichous flagella.
Physiologically, E. coli is versatile and well-adapted to its characteristic habitats. It can grow in media with glucose as the sole organic constituent. Wild-type E. coli has no growth factor requirements, and metabolically it can transform glucose into all of the macromolecular components that make up the cell. The bacterium can grow in the presence or absence of O2. Under anaerobic conditions it will grow by means of fermentation, producing characteristic "mixed acids and gas" as end products. However, it can also grow by means of anaerobic respiration, since it is able to utilize NO3, NO2 or fumarate as final electron acceptors for respiratory electron transport processes. In part, this adapts E. coli to its intestinal (anaerobic) and its extraintestinal (aerobic or anaerobic) habitats.
E. coli can respond to environmental signals such as chemicals, pH, temperature, osmolarity, etc., in a number of very remarkable ways considering it is a single-celled organism. For example, it can sense the presence or absence of chemicals and gases in its environment and swim towards or away from them. Or it can stop swimming and grow fimbriae that will specifically attach it to a cell or surface receptor. In response to change in temperature and osmolarity, it can vary the pore diameter of its outer membrane porins to accommodate larger molecules (nutrients) or to exclude inhibitory substances. With its complex mechanisms for regulation of metabolism the bacterium can survey the chemical contents its environment in advance of synthesizing any enzymes necessary to use these compounds. It does not wastefully produce enzymes for degradation of carbon sources unless they are available, and it does not produce enzymes for synthesis of metabolites if they are available as nutrients in the environment.
E.coli on Blood Plate Agar
References
Textbookofbacteriology
Singapore General Hospital Protocol Document No. 70300-13W-411
Friday, December 8, 2006
daphne patient 2 - 2nd posting
Salmonella
One of the most common pathogens found in people who are diagnosed with diarrhea is Salmonella. Below is a brief overview of this pathogen and some of its characteristics .
Characteristics
Salmonella is a Gram-negative facultative rod-shaped bacterium in the same proteobacterial family as Escherichia coli, the family Enterobacteriaceae, trivially known as "enteric" bacteria. Salmonella is nearly as well-studied as E. coli from a structural, biochemical and molecular point of view, and as poorly understood as E. coli from an ecological point of view. Salmonellae live in the intestinal tracts of warm and cold blooded animals. Some species are ubiquitous. Other species are specifically adapted to a particular host. In humans, Salmonella are the cause of two diseases called salmonellosis: enteric fever (typhoid), resulting from bacterial invasion of the bloodstream, and acute gastroenteritis, resulting from a foodborne infection/intoxication.
Salmonella Nomenclature
The genus Salmonella is a member of the family Enterobacteriaceae, It is composed of bacteria related to each other both phenotypically and genotypically. Salmonella DNA base composition is 50-52 mol% G+C, similar to that of Escherichia, Shigella, and Citrobacter. The bacteria of the genus Salmonella are also related to each other by DNA sequence. The genera with DNA most closely related to Salmonella are Escherichia, Shigella, and Citrobacter. Similar relationships were found by numerical taxonomy and 16S ssRNA analysis.
Salmonella nomenclature has been controversial since the original taxonomy of the genus was not based on DNA relatedness, rather names were given according to clinical considerations, e.g., Salmonella typhi, Salmonella cholerae-suis, Salmonella abortus-ovis, and so on. When serological analysis was adopted into the Kauffmann-White scheme in 1946, a Salmonella species was defined as "a group of related fermentation phage-type" with the result that each Salmonella serovar was considered as a species. Since the host-specificity suggested by some of these earlier names does not exist (e.g., S. typhi-murium, S. cholerae-suis are in fact ubiquitous), names derived from the geographical origin of the first isolated strain of the newly discovered serovars were next chosen, e.g., S. london, S. panama, S. stanleyville.
Susequently it was found that all Salmonella serovars form a single DNA hybridization group, i.e., a single species composed of seven subspecies, and thenomenclature had to be adapted. To avoid confusion with the familiar names of serovars, the species name Salmonella enterica was proposed with the following names for the subspecies:
enterica I
salamae II
arizonae IIIa
diarizonae IIIb
houtenae IV
bongori V
indica VI
Each subspecies contains various serovars defined by a characteristic antigenic formula.
Since this formal Latin nomenclature may not be clearly understood by physicians and epidemiologists, who are the most familiar with the names given to the most common serovars, the common serovars names are kept for subspecies I strains, which represent more than 99.5% of the Salmonella strains isolated from humans and other warm-blooded animals. The vernacular terminology seems preferred in medical practice, e.g., Salmonella ser. Typhimurium (not italicized) or shorter Salmonella (or S.) Typhimurium.
Habitats
The principal habitat of the salmonellae is the intestinal tract of humans and animals. Salmonella serovars can be found predominantly in one particular host, can be ubiquitous, or can have an unknown habitat. Typhi and Paratyphi A are strictly human serovars that may cause grave diseases often associated with invasion of the bloodstream. Salmonellosis in these cases is transmitted through fecal contamination of water or food. Gallinarum, Abortusovis, and Typhisuis are, respectively, avian, ovine, and porcine Salmonella serovars. Such host-adapted serovars cannot grow on minimal medium without growth factors (contrary to the ubiquitous Salmonella serovars).
Ubiquitous (non-host-adapted) Salmonella serovars (e.g., Typhimurium) cause very diverse clinical symptoms, from asymptomatic infection to serious typhoid-like syndromes in infants or certain highly susceptible animals (mice). In human adults, ubiquitousi organisms are mostly responsible for foodborne toxic infections.
The pathogenic role of a number of Salmonella serovars is unknown. This is especially the case with serovars from subspecies II to VI. A number of these serovars have been isolated rarely (some only once) during a systematic search in cold-blooded animals.
Salmonella in the Natural Environment
Salmonellae are disseminated in the natural environment (water, soil, sometimes plants used as food) through human or animal excretion. Humans and animals (either wild or domesticated) can excrete Salmonella either when clinically diseased or after having had salmonellosis, if they remain carriers. Salmonella organisms do not seem to multiply significantly in the natural environment (out of digestive tracts), but they can survive several weeks in water and several years in soil if conditions of temperature, humidity, and pH are favorable.
Isolation and Identification of Salmonella
A number of plating media have been devised for the isolation of Salmonella. Some media are differential and nonselective, i.e., they contain lactose with a pH indicator, but do not contain any inhibitor for non salmonellae (e.g., bromocresol purple lactose agar). Other media are differential and slightly selective, i.e., in addition to lactose and a pH indicator, they contain an inhibitor for nonenterics (e.g., MacConkey agar and eosin-methylene blue agar).
The most commonly used media selective for Salmonella are SS agar, bismuth sulfite agar, Hektoen enteric (HE) medium, brilliant green agar and xylose-lisine-deoxycholate (XLD) agar. All these media contain both selective and differential ingredients and they are commercially available.
Media used for Salmonella identification are those used for identification of all Enterobacteriaceae. Most Salmonella strains are motile with peritrichous flagella, however, nonmotile variants may occur occasionally. Most strains grow on nutrient agar as smooth colonies, 2-4 mm in diameter. Most strains are prototrophs, not requiring any growth factors. However, auxotrophic strains do occur, especially in host-adapted serovars such as Typhi and Paratyphi A.
Pathogenesis of Salmomella Infections in Humans
Salmonella infections in humans vary with the serovar, the strain, the infectious dose, the nature of the contaminated food, and the host status. Certain serovars are highly pathogenic for humans; the virulence of more rare serovars is unknown. Strains of the same serovar are also known to differ in their pathogenicity. An oral dose of at least 105Salmonella Typhi cells are needed to cause typhoid in 50% of human volunteers, whereas at least 109 S. Typhimurium cells (oral dose) are needed to cause symptoms of a toxic infection. Infants, immunosuppressed patients, and those affected with blood disease are more susceptible to Salmonella infection than healthy adults.
In the pathogenesis of typhoid the bacteria enter the human digestive tract, penetrate the intestinal mucosa (causing no lesion), and are stopped in the mesenteric lymph nodes. There, bacterial multiplication occurs, and part of the bacterial population lyses. From the mesenteric lymph nodes, viable bacteria and LPS (endotoxin) may be released into the bloodstream resulting in septicemia Release of endotoxin is responsible for cardiovascular “collapsus and tuphos” (a stuporous state—origin of the name typhoid) due to action on the ventriculus neurovegetative centers.
Salmonella excretion by human patients may continue long after clinical cure. Asymptomatic carriers are potentially dangerous when unnoticed. About 5% of patients clinically cured from typhoid remain carriers for months or even years. Antibiotics are usually ineffective on Salmonella carriage (even if salmonellae are susceptible to them) because the site of carriage may not allow penetration by the antibiotic.
Salmonellae survive sewage treatments if suitable germicides are not used in sewage processing. In a typical cycle of typhoid, sewage from a community is directed to a sewage plant. Effluent from the sewage plant passes into a coastal river where edible shellfish (mussels, oysters) live. Shellfish concentrate bacteria as they filter several liters of water per hour. Ingestion by humans of these seafoods (uncooked or superficially cooked) may cause typhoid or other salmonellosis. Salmonellae do not colonize or multiply in contaminated shellfish.
Typhoid is strictly a human disease.The incidence of human disease decreases when the level of development of a country increases (i.e., controlled water sewage systems, pasteurization of milk and dairy products). Where these hygienic conditions are missing, the probability of fecal contamination of water and food remains high and so is the incidence of typhoid.
Foodborne Salmonella toxic infections are caused by ubiquitous Salmonella serovars (e.g., Typhimurium). About 12-24 hours following ingestion of contaminated food (containing a sufficient number of Salmonella), symptoms appear (diarrhea, vomiting, fever) and last 2-5 days. Spontaneous cure usually occurs.
Salmonella may be associated with all kinds of food. Contamination of meat (cattle, pigs, goats, chicken, etc.) may originate from animal salmonellosis, but most often it results from contamination of muscles with the intestinal contents during evisceration of animals, washing, and transportation of carcasses. Surface contamination of meat is usually of little consequence, as proper cooking will sterilize it (although handling of contaminated meat may result in contamination of hands, tables, kitchenware, towels, other foods, etc.). However, when contaminated meat is ground, multiplication of Salmonella may occur within the ground meat and if cooking is superficial, ingestion of this highly contaminated food may produce a Salmonella infection. Infection may follow ingestion of any food that supports multiplication of Salmonella such as eggs, cream, mayonnaise, creamed foods, etc.), as a large number of ingested salmonellae are needed to give symptoms. Prevention of Salmonella toxic infection relies on avoiding contamination (improvement of hygiene), preventing multiplication of Salmonella in food (constant storage of food at 4°C), and use of pasteurized and sterilized milk and milk products. Vegetables and fruits may carry Salmonella when contaminated with fertilizers of fecal origin, or when washed with polluted water.
The incidence of foodborne Salmonella infection/toxication remains reletavely high in developed countries because of commercially prepared food or ingredients for food. Any contamination of commercially prepared food will result in a large-scale infection. In underdeveloped countries, foodborne Salmonella intoxications are less spectacular because of the smaller number of individuals simultaneously infected, but also because the bacteriological diagnosis of Salmonella toxic infection may not be available. However, the incidence of Salmonella carriage in underdeveloped countries is known to be high.
Salmonella epidemics may occur among infants in pediatric wards. The frequency and gravity of these epidemics are affected by hygienic conditions, malnutrition, and the excessive use of antibiotics that select for multiresistant strains.
Salmonella Enteritidis Infection
Egg-associated salmonellosis is an important public health problem in the United States and several European countries. Salmonella Enteritidis, can be inside perfectly normal-appearing eggs, and if the eggs are eaten raw or undercooked, the bacterium can cause illness. During the 1980s, illness related to contaminated eggs occurred mosy frequently in the northeastern United States, but now illness caused by S. Enteritidis is increasing in other parts of the country as well.
Unlike eggborne salmonellosis of past decades, the current epidemic is due to intact and disinfected grade A eggs. Salmonella Enteritidis silently infects the ovaries of healthy appearing hens and contaminates the eggs before the shells are formed. Most types of Salmonella live in the intestinal tracts of animals and birds and are transmitted to humans by contaminated foods of animal origin. Stringent procedures for cleaning and inspecting eggs were implemented in the 1970s and have made salmonellosis caused by external fecal contamination of egg shells extremely rare. However, unlike eggborne salmonellosis of past decades, the current epidemic is due to intact and disinfected grade A eggs. The reason for this is that Salmonella Enteritidis silently infects the ovaries of hens and contaminates the eggs before the shells are formed.
Although most infected hens have been found in the northeastern United States, the infection also occurs in hens in other areas of the country. In the Northeast, approximately one in 10,000 eggs may be internally contaminated. In other parts of the United States, contaminated eggs appear less common. Only a small number of hens seem to be infected at any given time, and an infected hen can lay many normal eggs while only occasionally laying an egg contaminated with Salmonella Enteritidis.
A person infected with the Salmonella Enteritidis usually has fever, abdominal cramps, and diarrhea beginning 12 to 72 hours after consuming a contaminated food or beverage. The illness usually lasts 4 to 7 days, and most persons recover without antibiotic treatment. However, the diarrhea can be severe, and the person may be ill enough to require hospitalization. The elderly, infants, and those with impaired immune systems (including HIV) may have a more severe illness. In these patients, the infection may spread from the intestines to the bloodstream, and then to other body sites and can cause death unless the person is treated promptly with antibiotics.
Exotoxins
Salmonella strains may produce a thermolabile enterotoxin that bears a limited relatedness to cholera toxin both structurally and antigenically. This enterotoxin causes water secretion in rat ileal loop and is recognized by antibodies against both cholera toxin and the thermolabile enterotoxin (LT) of enterotoxinogenic E. coli, but it does not bind in vitro to ganglioside GM1 (the receptor for E. coli LT and cholera ctx). Additionally, a cytotoxin that inhibits protein synthesis and is immunologically distinct from Shiga toxin has been demonstrated. Both of these toxins are presumed to play a role in the diarrheal symptoms of salmonellosis.
Antibiotic Susceptibility
During the last decade, antibiotic resistance and multiresistance of Salmonella spp. have increased a great deal. The cause appears to be the increased and indiscriminate use of antibiotics in the treatment of humans and animals and the addition of growth-promoting antibiotics to the food of breeding animals. Plasmid-borne antibiotic resistance is very frequent among Salmonella strains involved in pediatric epidemics (e.g., Typhimurium, Panama, Wien, Infantis). Resistance to ampicillin, streptomycin, kanamycin, chloramphenicol, tetracycline, and sulfonamides is commonly observed. Colistin resistance has not yet been observed.
Additional Info
Background: First described in 1880 and cultured in 1884, salmonellae are motile, gram-negative, rod-shaped bacteria of the family Enterobacteriaceae. Named after Daniel E. Salmon, the pathologist who first isolated the organism from porcine intestine, salmonellae are common in the gastrointestinal tracts of mammals, reptiles, birds, and insects.
As with the closely related bacterium Escherichia coli, salmonellae are potential enteric pathogens and a leading cause of bacterial food-borne illness. Additionally, salmonellae have been implicated in a spectrum of other diseases, including enteric or typhoid fever (primarily Salmonella typhi and Salmonella paratyphi), bacteremia, endovascular infections, focal infections (eg, osteomyelitis), and enterocolitis (typically Salmonella typhimurium, Salmonella enteritidis, and Salmonella heidelberg).
All salmonellae are grouped into a single overarching species. This species, Salmonella choleraesuis, is divided into 7 subgroups based on DNA homology and host range. Most of the salmonellae that are pathogenic in humans belong to a single subgroup (subgroup I). Additionally, each of the salmonellae can be serotyped according to their particular complement of somatic O, surface Vi, and flagellar H antigens. Presently, more than 2,300 Salmonella serovars exist.
Salmonellae can be isolated in the microbiology laboratory using a number of low-selective media (MacConkey agar, deoxycholate agar), intermediate-selective media (Salmonella-Shigella [SS] agar, Hektoen [HE] agar), and highly selective media (selenite agar with brilliant green). Individual isolates can then be distinguished by serotyping, bacteriophage typing, and genotyping.
Pathophysiology: The transmission of salmonellae to a susceptible host usually occurs by consumption of contaminated foods. The most common sources of salmonellae are beef, poultry, and eggs. In one recent estimate, consumption of egg shell fragments contaminated with Salmonella enterica serovar Enteritidis was responsible for approximately 182,060 cases of enteritis in the United States in the year 2000. Improperly prepared fruits, vegetables, dairy products, and shellfish have also been implicated as sources of Salmonella. Moreover, human-to-human and animal-to-human transmission can occur. For example, amphibian and reptile exposure is associated with approximately 74,000 Salmonella infections annually in the United States. Recently, cats have also been implicated as a potential reservoir.
Although the infectious dose varies among strains, a large inoculum is thought to be necessary to overcome stomach acidity and to compete with normal intestinal flora. Large inocula are also associated with higher rates of illness and shorter incubation periods. However, lower infectious doses may be adequate to cause infection if these organisms are co-ingested with foods that rapidly transit the stomach (eg, liquids) or that raise gastric pH (eg, cheese, milk), if antacids are used concomitantly, or if these organisms are ingested by individuals with impaired immune systems.
After ingestion, infection with salmonellae is characterized by attachment of the bacteria by fimbriae or pili to cells lining the intestinal lumen. Salmonellae selectively attach to specialized epithelial cells (M cells) of the Peyer patches. The bacteria are then internalized by receptor-mediated endocytosis and transported within phagosomes to the lamina propria, where they are released. Once there, salmonellae induce an influx of macrophages (typhoidal strains) or neutrophils (nontyphoidal strains). Although nontyphoid salmonellae generally precipitate a localized response, S typhi and other especially virulent strains invade deeper tissues via lymphatics and capillaries and elicit a major immune response.
Virulence factors of salmonellae are complex and encoded both on the organism's chromosome and on large (34-120 kd) plasmids. Some areas of active investigation include the means by which salmonellae attach to and invade the intestine, survive within phagosomes, effect a massive efflux of electrolytes and water into the intestinal lumen, and develop drug resistance. Several Salmonella pathogenicity islands have been identified that mediate uptake of the bacteria into epithelial cells (type III secretion system [TTSS]), nonphagocytic cell invasion (Salmonella pathogenicity-island 1 [SPI-1]), and survival and replication within macrophages (Salmonella pathogenicity-island 2 [SPI-2], phoP/phoQ).
The severity of illness in individuals infected with salmonellae is determined not only by the virulence factors of the infecting strain but by host properties as well. For example, individuals at the extremes of age (ie, people who are very young or very old) are at an increased risk for bacteremia. Similarly, systemic lupus erythematosus, malignancies, and immune deficiency are also associated with increased risk of bacteremia.
History: salmonella infections typically produce 1 of 3 distinct syndromes: gastroenteritis, typhoid (enteric) fever, or focal disease.
Infection with nontyphoidal salmonellae usually causes enterocolitis similar to that caused by other bacterial enteric pathogens.
Nausea, vomiting, and diarrhea occur within 6-48 hours after ingestion of contaminated food or drink.
In most cases, stools are loose and bloodless. Salmonellae may rarely cause large-volume choleralike diarrhea or may be associated with tenesmus.
The diarrhea is typically self-limiting and resolves within 3-7 days.
While an initial transient diarrhea may occur, established infections with S typhi or S paratyphi are associated with abdominal pain and either constipation (~40%) or recurrent diarrhea (~40%).
Fever, abdominal cramping, chills, headache, and myalgia are common.
Fever usually resolves within 48 hours.
Enteric fever (typically caused by S typhi or S paratyphi) is generally an acute illness manifested by fever, headache, and abdominal symptoms and should be considered in travelers returning from tropical and subtropical areas.
Focal disease is variable and defined by the site of infection.
Physical: Patients with Salmonella gastroenteritis typically have a self-limiting fever (38-39°C) within 48 hours of ingestion. A prolonged persistent fever (4-8 wk in untreated individuals) that increases daily (as high as 41°C) suggests typhoid fever. Nontyphoidal gastroenteritis is generally limited to diarrhea, although typhoid (enteric) fever may present with both gastrointestinal and skin manifestations (ie, rose spots). The following organ systems may be involved with Salmonella infection:
Gastrointestinal: Salmonella infections typically cause nonbloody loose stool or watery diarrhea. Abdominal tenderness (~50%) and mild hepatosplenomegaly (~50%) are both common in patients with typhoid fever.
Cardiovascular: Salmonella infections (commonly S typhimurium or S choleraesuis) may produce arterial infections or endocarditis.
Pulmonary: Salmonella pneumonia or empyema is rare in the absence of comorbid illnesses such as underlying lung disease, malignancy, diabetes, sickle cell anemia, or alcohol abuse.
Genitourinary: Individuals with urolithiasis or structural abnormalities or individuals who are undergoing immunosuppressive therapy are predisposed to Salmonella urinary tract infections.
Neurologic: Salmonella meningitis may rarely occur, typically in infants and young children.
Skeletal: Infection with salmonellae may cause septic arthritis and osteomyelitis. The latter affects the long bones and typically occurs in patients with sickle cell disease.
Integument: Enteric fever may be associated with pink, blanchable, slightly raised macules (rose spots) on the chest and abdomen.
The causative agent of typhoid fever is the bacterium Salmonella typhi. (Image courtesy of the Centers for Disease Control and Prevention
References:
>medlineplus>>ency>>imagepages>>1048.htm">http>>www.nlm.nih.gov>>medlineplus>>ency>>imagepages>>1048.htm
>MED>>topic2058.htm">http>>www.emedicine.com>>MED>>topic2058.htm
Patient 1 Khong Fay Fay
Cystitis is the most common urinary tract infection and is sometimes referred to as acute uncomplicated UTI. It occurs in the lower urinary tract (the bladder and urethra) and nearly always in women.
Bacterial Strains in Acute Uncomplicated UTI(cystitis). The bacterial strains likely to cause acute uncomplicated UTI are the following:
- E. coli. is responsible for between 72% and 85% of cystitis cases in younger women, and more than 50% in women over 50. In most cases of UTI, E. coli, which originates as a harmless micro-organism in the intestines, spreads to the vaginal passage, where it invades and colonizes the urinary tract. One study suggests that even when infected cells lining the bladder die and slough off, carrying the E. coli bacteria with them, some bacteria can invade into deeper tissue in the bladder, where they survive to reinfect the patient later on.
- Staphylococcus saprophyticus may be another common culprit, especially in younger women. Interestingly, infections caused by this bacteria have a seasonal variation, with a higher incidence in the summer and fall than in the winter and spring.
- Klebsiella and enterococci bacteria are often found in UTIs in older women.
- Proteus mirabilis is the other common bacterium associated with these infections.
- Pseudomonas aeruginosa is a rare bacterial cause and is most often detected in hospital-acquired UTIs. Since this patient is not admitted, this organism is ruled out.
- Some evidence suggests that Ureaplasma urealyticum and Mycoplasma hominis, which are generally harmless organisms, may be responsible for occasional urinary tract disorders.
- Complicated UTIs, which are related to physical or structural conditions, are apt to be caused by a wider range of organism. E. coli is still the most common organism, but others have also been detected, including the following: Other intestinal bacteria, including klebsiella, P. mirabilis, and citrobacter.
- Fungal organisms, particularly candida species. (Candida albicans, for example, causes the "yeast infections" that also occur in the mouth, digestive tract, and vagina.)
- Others include Pseudomonas aeruginosa, enterobacter, and serratia species; gram-positive organisms, including enterococcus species; and S. saprophyticus.
From the above most common organisms that are found in the Urinary Tract Infection the ones that are suspected are as follows ;
- Escherichia Coli
- Staphylococcus saprophyticus
- Proteus mirabilis
- Ureaplasma urealyticum and Mycoplasma hominis (she could be sexually-active)
Tests done to confirm the identity of the organism
A midstream urine specimen of 2 – 15 ml should be collected in a sterile plastic wide-mouthed container.
Dipstick tests are increasingly used to obtain a diagnosis of UTIs and are now available in drug stores without a prescription. The test employ a chemical that reacts to nitrites, substances produced by many of the bacteria that cause UTIs. This chemical is available on a stick that is dipped into a urine sample. In women with symptoms, the dipstick is proving to be a quick and practical way to identify most cases of infection.
A urinalysis involves a physical and chemical examination of urine. In addition, the urine is spun in a centrifuge to allow sediments containing blood cells, bacteria, and other particles to collect. This sediment is then examined under a microscope. A urinalysis, then, offers a number of valuable clues for an accurate diagnosis:
- Simply observing the urine for color and cloudiness can be important.
- Acidity is measured.
- White blood cells (leukocytes) are counted. A high count in the urine is referred to as pyuria. (A leukocyte count of over 10 per microliter of urine indicates pyuria.) Pyuria is usually sufficient for a diagnosis of UTI in nonhospitalized patients if standard symptoms (or just fever in small children) are also present.
Thursday, December 7, 2006
Patient 4-Ng Ming En (Nora)
Complaints: Severe vomiting, diarrhea, abdominal cramps
Diagnosis: Food poisoning
Food Poisoning is the result of eating organisms or toxins in contaminated food. Based on the patient’s complaints, the food poisoning can be caused by these microorganisms: Staphylococcus aureus, Vibrio cholerae, and Bacillus cereus.
1. S. aureus
•Normally found in ham, poultry, egg dishes, and pastries.
•S. aureus food poisoning is often caused when a food handler contaminates food products that are served or stored at room temperature. After the staphylococci have been introduced into the food, the food must remain at room temperature or warmer for the organisms to grow and release the toxin. Subsequent heating of the food will kill the bacteria but not inactivate the heat stable toxin.
•There are multiple enterotoxins: A-E, G-I, K-. The enterotoxins are heat stable and resistant to the action of gut enzymes. The enterotoxins is preformed in foods and has a short incubation period (1-8 hours)
•S. aureus food poisoning is characterized by severe vomiting, watery diarrhea, and abdominal pain. The emetic effect of enterotoxins is probably the result of central nervous system stimulation after the toxin acts on the neuron receptors in the guts. The enterotoxins genes will interact with accessory genetic elements (bacteriophages) to produce the toxins.
•Specimens are cultured on BAP at 370C for at least 18 hours. Young cocci stain strongly positive, on aging, many become negative. S. aureus produce catalase and coagulase.
•Susceptibility testing: resistance to Penicillin G can be predicted by a positive test for Beta-lactamase. Resistance to nafcillin and methicillin occurs in about 20%.
S. aureus on BAP (http://www2.umdnj.edu)
2. V. cholerae
•Normally found in shellfish
•When V. cholerae is ingested, it will colonies the small intestine.
•It is a non-invasive and causes disease by producing enterotoxins, called choleragen (heat labile toxin). These toxins can cause watery diarrhea (rice-waster stool). This is because the toxins will result in excess secretion of calcium ions into the intestinal lumen. Water, sodium, potassium and bicarbonate all follow due to concentration and electrical gradients.
•V. cholerae is a gram negative bacilli, and when a smear is done, dark field or phase contrast microscopy may show the rapidly motile Vibrio
•Specimen is to be cultured on TCBS; forms yellow colonies that are readily visible against the dark green background of the agar. For enrichment, a few drops of stool can be incubated for 6-8 hours in taurocholate-peptone broth (pH 8.0-9.0). And this can be used for staining and subculturing. V. cholera is oxidase positive.
•Confirmatory test: further identified by slide agglutination tests using anti-O group 1 antisera.
V. cholerae on TCBS (http://www.chp.gov.hk):
B. cereus
-associated with the consumption of cereals and cooked food (Chinese fried rice syndrome)
•Food poisoning caused by B. cereus has 2 distinct forms: the emetic type and the diarrheal type. The emetic type begins 1-5hours after ingestion of rice. When rice are cooked and allowed to cool slowly, the B. cereus spores germinate and the vegetative cells produce the toxins during log phase growth or during sporulation. The diarrheal form has an incubation period of 1-24 hours. The enterotoxin may be preformed in the food or produced in the intestine.
•Specimen is to be cultured on BAP. Strong Beta-hemolysis and irregular colonies are noted. B. cereus is catalase positive, and can be non-motile or motile.spore-forming, facultatively anaerobic rod.
•B. cereus can also be confirmed using immunological detection (http://www.rci.rutgers.edu)
click on this link: http://i17.tinypic.com/2mowfg6.jpg
Bacillus cereus on BAP (http://en.wikipedia.org)
References:
1. Brooks, G. F., Butel, J. S. & Ornston, L. N.; “Jawetz, Melnick & Adeberg’s Medical Microbiology”
2. Patrick R. Murray, Ken S. Rosenthal, George S. Kobayashi, Micheal A. PFaller.; "Medical Microbiology"
3. Monica Gandhi, Paul Baun, C Bradley Hare, Aaron B Caughey.; "Microbiology and Immunology"
Poated by Nora
Additional Information
Viral infections make up perhaps one third of cases of food poisoning in developed countries (In the US more than 50% of cases are viral). They are usually of intermediate (1-3 days) incubation period, cause illnesses which are self-limited in otherwise healthy individuals, and are similar to the bacterial forms described above.
1)Rotavirus
2)Norovirus (formerly Norwalk virus)
3)Rotavirus
4)Hepatitis A (distinguished from other viral causes by its prolonged (2-6 week) incubation period and its ability to spread beyond the stomach and intestines, into the liver)
5)Hepatitis E
Source http://en.wikipedia.org/wiki/Food_poisoning
posted by JT
Patient 5 Continued..
For this week, I am going to elaborate on some of the keywords mentioned in my previous entry and in addition, suspected micro-organisms will also be listed down, including the tests to be done and the expected results.
(a) Urethritis
Urethritis is inflammation of the urethra from any cause, which may include bacteria or a virus. The same bacteria that cause UTI (E. coli) and some sexually transmitted diseases (chlamydia, gonorrhea) can lead to urethritis. Viral causes of urethritis include herpes simplex virus and cytomegalovirus.
Source: (http://www.nlm.nih.gov/ > Medline > Medical Encycopedia > U > Urethritis)
(b) Cystitis (Recurrent)
Recurrent cystitis consists of at least 2 infections of the bladder in 6 months, or 3 infections in 1 year. It is confirmed by tests that show the growth of bacteria in the urine.Recurrent cystitis is most often caused E. coli, the leading cause of all UTIs. About 25-50% of all young, healthy women who suffer their first infection will develop a second one within 6 months. Although the risk for cystitis increases with age, the incidence of recurrent infections is only about 10-20% for people over 60.
Source: (http://www.nlm.nih.gov/ > Medline > Medical Encycopedia > Cp-Cz > Recurrent Cystitis)
(c) Pyelonephritis
Pyelonephritis is an infection of the kidney and the ducts that carry urine away from the kidney (ureters). It often occur as a result of UTI particularly in the presence of occasional or persistent backflow of urine from the bladder into the ureters or kidney pelvis.
Source: (http://www.nlm.nih.gov/ > Medline > Medical Encycopedia > Pm- Pz > Pyelonephritis)
(d) Asymptomatic UTI
When a person has no symptoms of infection but significant numbers of bacteria have colonized the urinary tract, the condition is called asymptomatic UTI (also called asymptomatic bacteriuria). (In general, there must be at least 100,000 bacteria per milliliter of urine.) The condition is harmless in most people and rarely persists, although it does increase the risk for developing symptomatic UTIs. Asymptomatic bacteriuria may be an indicator for serious health problems in the elderly, but screening for the condition is not warranted in this group.
(e) Complicated UTI
Complicated infections, which occur nearly as often in men as women, are also caused by bacteria but they occur as a result of some anatomical or structural abnormality. Often they are associated with catheter use in the hospital setting, bladder and kidney dysfunction, or kidney transplant (especially in the first three months after transplant). Recurrences occur in up to 50% to 60% of patients with complicated UTI if the underlying structural or anatomical abnormalities are not corrected.
Source: http://www.morehead.org/wellconnected/000036.htm
The micro-organisms suspected are Escherichia coli ( E. Coli) and Proteus Mirabilis respectively.
(1) Escherichia Coli
E. coli are facultatively anaerobic gram-negative rods that live in the intestinal tracts of animals and humans . They can grow in the presence or the absence of oxygen. Under anaerobic conditions, E. coli grow by fermentation, producing mixed acids and gases as end products. They can also grow by anaerobic respiration, utilizing NO3, NO2, or fumarate. This versatility is what gives E. coli its ability to adapt to its intestinal (anaerobic) and its extraintestinal (aerobic or anaerobic) habitats.
Source: (http://www.answers.com/main/ > Directory > Health > Encylcopedia of Health > E.Coli)
(1.1) Tests/ Expected Results
- Methly Red Positive and VogUes-Proskauer Negative
- Oxidase Negative
- Catalase Positive
Source: http://biology.fullerton.edu/biol302/302labf99/biochem.html
(2) Proteus Mirabilis
Proteus Mirabilis is a Gram- Negative, facultatively anaerobic bacterium. It shows swarming. motility and urease activity. P. mirabilis causes 90% of all 'Proteus' infections. It belongs to the Tribe Proteae.
(2.1) Diagnosis
An alkaline urine sample is a possible sign of P. mirabilis, which can be diagnosed in the lab due to characteristic swarming motility, and inability to metabolize lactose.
(2.2) Characteristics
P. mirabilis can utilize Urea and Citrate. It can produce Hydrogen Sulfide gas, and forms clear films on growth media. It is motile, possessing peritrichous flagella, and is known for its swarming ability. It is commonly found in the intestinal tract of humans.
(2.3) Tests/ Expected Results
- Indole Negative and Nitrogen Reductase Positive
- Methyl Red Positive and Vogues-Proskauer Negative
- Catalase Positive and Cytochrome Oxidase Negative
- Phenylalanine Deaminase positive
Source: (http://www.answers.com/main/ > Directory > References > Wikipedia > Proteus Mirabilis)
Indole Test, Methyl Red, Vogues- Proskauer (in order)
JUSTIFICATION
E. Coli accounts for <= 70% of bacteriuria in elderly female outpatients with uncomplicated sporadic cystitis and for about 40% in patients with indwelling bladder catheters, complicated infections, or nosocomial infections. P.mirabilis are more common in men than in women because these species tend to dominate the normal aerobic preputial flora.
Monday, December 4, 2006
Patient 1

Introduction
The urinary system consists of the kidneys, ureters, bladder, and urethra. The key elements in the system are the kidneys, a pair of purplish-brown organs located below the ribs toward the middle of the back. The kidneys remove excess liquid and wastes from the blood in the form of urine, keep a stable balance of salts and other substances in the blood, and produce a hormone that aids the formation of red blood cells. Narrow tubes called ureters carry urine from the kidneys to the bladder, a sack-like organ in the lower abdomen. Urine is stored in the bladder and emptied through the urethra. (http://kidney.niddk.nih.gov/kudiseases/pubs/utiadult/)
One woman in five develops a UTI during her lifetime. Women tend to get them more often because their urethra is shorter and closer to the anus. UTIs in men are not as common as in women but can be very serious when they do occur.
Causes
Usually urine is sterile, free from fungi, bacteria or viruses. An infection only occurs after microbes, usually bacteria present in the gut manage to cling onto the urethra and begin to multiply.
Escherichia (E.) coli is responsible for between 75% and 90% of uncomplicated cystitis cases in younger women and in more than half the cases in older women. Staphylococcus saprophyticus accounts for 5% to 15% of UTIs, mostly in younger women. Klebsiella, Enterococci bacteria, and Proteus mirabilis account for most of remaining bacterial agents that cause UTIs. They are generally found in UTIs in older women.
Rare bacterial causes of UTIs include ureaplasma urealyticum and Mycoplasma hominis, which are generally harmless organisms.
Organisms responsible for UTI:
- Bacteria
- Escherichia coli
- Proteus mirabilis
- Klebsiella
- Pseudomonas aeruginosa
- Serratia
- Enterobacter
- Staphylococcus epidermis
- Enteroccocus
- Salmonella typhi
- Mycobacterium tuberculosis
- Staphylococcus aureus
- Viruses
- Polyomavirus JC
- Polyomavirus BK
- Cytomegalovirus
- Adenovirus
- Fungi
- Candida albicans and other Candida spp.
- Histoplasma capsulatum
Source : http://everything2.com/index.pl?node=urinary%20tract%20infection
Sample Collection
A midstream urine specimen of 2 – 15 ml should be collected in a sterile plastic wide-mouthed container. It should reach the laboratory within 2 hours of collection; otherwise refrigeration (for up to 24 hours) is advised. Relevant clinical information should be provided along with the patient sample.
Diagnosing
UFEME
The urine specimen must first be dip tested for the presence of blood cells, both erythrocytes and leukocytes, nitrates and protein. It should then be sent of to the microbiology lab for culturing and antibiotic susceptibility tests.
A high count of leukocytes in the urine is referred to as pyuria. (A leukocyte count over 10 per microliter is considered to indicate pyuria.) This is very accurate in identifying the disease when it's present, but it also tests positive in many people who do not have a UTI. Pyuria is usually sufficient for a diagnosis of UTI in nonhospitalized patients if other standard symptoms (or just fever in small children) are also present.
Culture
The agar plates that are used in the culture of the microbe of the urine specimen are Blood agar, MacConkey agar and Cled agar. UTI is nearly always caused by a single species of bacteria, notably E. coli.
MacConkey – Differentiate between Gram-negative by inhibiting the growth of Gram-positive bacteria.
Blood – is a differential media used to isolate fastidious organisms and detect hemolytic activity.
Cled – isolation and differentiation of urinary organisms.
If microorganisms, are isolated, they are then identified by performing biochemical tests. Normally, a gram stain is done first. Depending on their colour stain, shape and their gram category, biochemical tests are done to determine their identity. Just to name a few, a catalase or coagulase test might have to be performed.
Sensitivity
After cultivation on the agar plates, the organism is then checked for resistance to any type of antibiotics. This will assist the clinician in prescribing the right type of drug to the patient for quick recovery.
aFzAL